This article has been published by the International Biopharmaceutical Association www.ibpassociation.org
The project is sponsored by KRC CRO and training services (www.kriger.com ) and ClinQua CRO (www.clinqua.com )
Start your Clinical Research Career Now
Background
Divided by mode of action
1. inhibit cell wall synthesis – penicillins, cephalosporins, carbapenems, vancomycin, bacitracin, miconazole, ketoconazole, clotrimazole
2. increase permeability of cell membrane – polymyxin, nystatin, amphotericin B
3. reversibly inhibit protein synthesis by affecting ribosomes 30 S and 50 S (bacteriostatic) – chloramphenicol, tetracyclines, macrolides, clindamycin
4. alter protein synthesis via 30 S ribosomes (bactericidal) – aminoglycosides
5. inhibit nucleic acids – rifampin, quinolones
6. antimetabolites – trimethoprim, sulfonamides
7. nucleic acid analogs – act on viruses – acyclovir, zidovudine, ganciclovir
Scanning electron m icrographs illustrating external features of the rod-shaped bacterium E. coli. The top image above is from: http://www.uq.oz.au/nanoworld. The lower image above is from: http://www.slic2.wsu.edu:82/hurlbert/micro101/pages/Chap2.html#two_bact_groups
PENICILLINS (Beta Lactams)
General side-effects
1. Most important are hypersensitivity and anaphylaxis. Penicillins are the most common cause of drug allergy. All types, dosages and forms of administration can potentially cause allergic reactions. Cross-reactions among the penicillins and between them and the cephalosporins are not uncommon.
2. Local reactions to intramuscular injection may be seen. Oral administration may cause nausea and diarrhea.
3. Toxic effects are minimal.
Penicillin G and V
1. effective against
a. Gram-positive cocci (Streptococcus, Neisseria meningitidis, but not Enterococcus)
b. Trepenoma pallidum (syphilis)
c. Borrelia burgdorferi (Lyme disease)
d. some anaerobes (Clostridium, Corynebacterium diphtheriae, Actinomyces, Bacillus anthracis, Listeria) – not Bacteroides fragilis
2. Susceptible to penicillinase and so not effective against Staphylococcus aureus
3. Given orally (penicillin V less vulnerable to gastric acid) orparenterally; adding procaine or benzathine prolongs the effect of the penicillin. Best absorption is on an empty stomach.
4. Uses
a. To treat infections by above bacteria
b. As prophylaxis to prevent recurrent rheumatic fever, and in contacts of patients with syphilis, gonorrhea and streptococcal infections
c. Used as prophylaxis for infective endocarditis for susceptible people before dental or surgical procedures
5. Interactions – probenecid causes increased concentration
6. Jarisch-Herxheimer reaction
a. Seen in the majority of patients with secondary syphilis on receiving the first dose of penicillin
b. Flu-like symptoms – chills, fever, muscle aches, headache, joint pain – with enhanced color of the lesions of syphilis
c. Lasts for up to 48 hours and does not recur with later doses
d. May be due to antigens released by breakdown of the spirochetes
e. Not a reason to stop penicillin treatment; aspirin will help with symptoms
Penicillinase-resistant penicillins
1. Examples are methicillin, nafcillin, oxacillin, cloxacillin, and dicloxacillin
2. Effective against Gram-positive cocci (less so than penicillin V or G), including Staphylococcus aureus
3. MRSA = methicillin resistant S. aureus are treated by vancomycin.
4. Given orally (best absorption is on an empty stomach) andparenterally
5. Methicillin may cause interstitial nephritis.
Ampicillin, etc.
1. Examples are ampicillin, amoxicillin, bacampicillin
2. Effective also against some Gram-negative organisms – i.e. Hemophilus, E. coli, Proteus, also Salmonella and Listeria
3. Susceptible to b-lactamase – and so not effective for Staph. infections
4. Given orally (best is on an empty stomach) and parenterally
5. Ampicillin causes a rash in patients with infectious mononucleosis. Allopurinol will also increase chances of a rash with ampicillin.
Ampicillin and clavulanic acid
1. Clavulanic acid inactivates b-lactamase and so prevents breakdown of the antibiotic
2. Thus, the compound is effective against Staph. organisms.
Anti-Pseudomonas penicillins
1. Examples are carbenicillin and ticarcillin
2. Effective also against Pseudomonas, Enterobacter and Proteus
3. Susceptible to b-lactamase
4. Carbenicillin increases risk of heart failure, due to its ability to causehypernatremia and hypokalemia. It also interferes with aggregation of platelets. Ticarcillin has fewer side effects and so is preferred; it is given orally and parenterally.
5. A preparation of ticarcillin and clavulanic acid (for parenteral use) is more effective against Bacteroides, S. aureus and Gram-negative bacilli.
Broad-spectrum penicillins
1. Examples are mezlocillin and piperacillin
2. Effective also against Klebsiella and some other Gram-negative organisms
3. Susceptible to b-lactamase
4. Given only parenterally
CEPHALOSPORINS
General information
1. Most are given orally, intramuscularly or intravenously. Cephalothin is painful when injected intramuscularly and so should be used intravenously only.
2. Need to reduce dose in cases of kidney dysfunction
3. Cefuroxime, moxalactam, cefotaxime, ceftriaxone, cefepime and ceftizoxime are found in therapeutic concentrations in the Cerebrospinal Fluid (CSF).
4. Cephalosporins cross the placenta.
5. Uses
a. As treatment for bacteria as given below
b. Prophylaxis for surgery
6. Side effects
a. Hypersensitivity reactions, as with penicillins; is cross-reactivity with penicillins
b. Diarrhea
7. Toxic effects – renal damage including acute tubular necrosis
8. Interactions - risk of nephrotoxicity increased with aminoglycosides
First generation
1. Examples are cephalothin, cefazolin, cephalexin and cefadroxil. The first two are given parenterally, the second two orally.
2. Effective against Gram-positive organisms (not including MRSA, S. epidermidis or Enterococcus) with slight activity against Gram-negative organisms (E. coli, Moraxella, Klebsiella, Proteus)
Second generation
1. Examples are cefoxitin, cefotetan, cefmanadole, cefuroxime, cefonicid and ceforanide that are given parenterally and cefaclor and loracarbef that can be given orally.
2. More effective against Gram-negative and less against Gram-positive than first generation cephalosporins; some are good against Bacteroides
Third generation
1. Examples are ceftazidime, cefoperazone, cefotaxime, ceftizoxime and ceftriaxone that are given parenterally, and cefpodoxime that can be given orally.
2. More effective against Gram-negative and less against Gram-positive than second generation cephalosporins, especially Enterobacter; some are good against Pseudomonas
3. Moxalactam can cause extensive hemorrhage.
Fourth generation
1. The only example available is cefepime, given parenterally.
2. Wider range than third generation and more stable against b-lactamase
CARBAPENEMS
Imipenem
1. A b-lactam antibiotic with a wide spectrum of activity; mode of action like penicillins and cephalosporins
2. Used when other antibiotics fail to eradicate bacteria
3. Given intravenously together with cilastin to prevent breakdown in the renal tubules
Aztreonam
1. Also wide spectrum, and not usually first line antibiotic
2. Activity mostly against Gram-negative organisms – especially Enterobacter and Pseudomonas
SULFONAMIDES AND TRIMETHOPRIM-SULFAMETHOXAZOLE (=CO-TRIMOXAZOLE)
1. Bacteriostatic against a wide range of Gram-positive and Gram-negative, but many organisms are resistant
2. Act by preventing synthesis of folic acid
3. Trimethoprim and sulfamethoxazole (a sulfonamide) together are synergistic in inhibiting folic acid and bacteria show less resistance.
4. Good oral absorption
5. Important for patient to be well hydrated and dose reduced (or avoided) in patient with renal insufficiency
6. Uses – used less these days, as bacteria become resistant
a. Sulfonamides are effective against Nocardia and Toxoplasma.
b. Can replace penicillin for prophylaxis in penicillin-sensitive patients
7. Side effects
a. Lack of appetite, nausea and vomiting
b. Can cause kernicterus in neonate if given to neonate or pregnant woman
c. Headache, depression, hallucinations
8. Toxic effects – hypersensitivity reactions, agranulocytosis, aplastic anemia
9. Contraindication – patients with G6PD deficiency – may cause acute hemolysis
10. Interactions – can increase effects of oral anticoagulants, sulfonylureas and hydantoin
11. Examples
a. Sulfisoxazole – used topically in the eye, with erythromycin for otitis media and for urinary tract infections.
b. Sulfasalazine is used in inflammatory bowel disease. Side-effects include nausea, fever, joint pain and rash. Toxic reactions include anemia and agranulocytosis.
c. Sulfacetamide is used topically in the eye.
d. Silver sulfadiazine is used on burns or decubitus (pressure) ulcers to prevent secondary bacterial or fungal infection
e. Trimethoprim-sulfamethoxazole is used in pediatric infections and in urinary tract infections and gastroenteritis. It is also effective against Pneumocystis carinii in AIDS patients. It is used for prophylaxis in neutropenic patients.
QUINOLONES
1. Examples are ciprofloxacin, ofloxacin and norfloxacin.
2. Act by inhibiting DNA gyrase
3. Well absorbed orally; also given parenterally
4. Effective against E. coli, Shigella, Salmonella, Enterobacter, Campylobacter and Neisseria. Ciprofloxacin is more effective against Pseudomonas, Enterococcus and Pneumococcus. Quinolones also effective against intracellular bacteria such as Chlamydia, Mycoplasma, Mycobacterium, Legionella and Brucella.
5. Uses - urinary tract infections, prostatitis, sexually-transmitted diseases, gastroenteritis
6. Side effects
a. Nausea, headache, dizziness, abdominal discomfort
b. Can increase risk of convulsions in patient with epilepsy
7. Interactions
a. Theophylline or non-steroidal anti-inflammatory drugs (NSAIDs) with a quinolone can cause hallucinations, delirium and even seizures.
b. Ciprofloxacin increases concentration of theophylline.
8. Contraindicated in children, pregnant or nursing women, and in epileptics.
DRUGS SPECIFIC FOR URINARY TRACT INFECTIONS
1. Concentration in urine with minimal systemic effects after oral administration
2. Examples are nalidixic acid, nitrofurantoin and methenamine.
AMINOGLYCOSIDES
General information
1. Examples are gentamicin, netilmicin, amikacin, streptomycin, tobramycin and neomycin.
2. Effective against aerobic Gram-negative organisms; amikacin has the widest spectrum
3. Not absorbed orally; given parenterally or topically
4. Uses
a. Gentamicin, tobramycin, amikacin and netilmicin are all used inpyelonephritis, hospital-acquired pneumonia, meningitis (by Gram-negative bacteria, given intrathecally), peritonitis, sepsis.
b. Tobramycin is also used topically in the eye.
c. Streptomycin was the prototype; due to resistance, it is now used mostly in tuberculosis, tularemia and plague
d. Neomycin is used only topically or orally (to clean the intestines before abdominal surgery) because of its severe toxicities.
5. Toxic effects
a. Ototoxicity – act on both auditory and vestibular portions of cranial nerve VIII, damage is usually irreversible, main effect is hearing loss
b. Nephrotoxicity – usually mild and reversible; the main problem is decreased clearance increases risk of ototoxicity
c. Rare – neuromuscular blockade with apnea
d. Streptomycin may also cause damage to the optic nerve and peripheral neuritis
4. Interactions - Furosemide and ethacrynic acid are synergistic for hearing loss with aminoglycosides.
TETRACYCLINES
1. Broad spectrum – bacteriostatic against Gram-positive and Gram-negative organisms, including Rickettsia, Chlamydia, Mycoplasma pneumoniae, Brucella, Hemophilus ducreyi, Legionella, Helicobacter pylori, Trepenoma pallidum, Borrelia bungdorferi and Ureaplasma
2. Examples are tetracycline, doxycycline, minocycline and demeclocycline.
3. Usually given orally; can be parenterally or topically to the eye
4. Uses – for treatment of infections by the above bacteria and also for the treatment of acne
5. Side effects
a. Damages intestinal flora and may cause fungal overgrowth, cause nausea, vomiting, diarrhea epigastric pain and abdominal discomfort (better if given with food); esophagitis and ulcers have been seen.
b. Severe thrombophlebitis may occur with intravenous use.
c. Demeclocycline and doxycycline may cause photosensitivity.
6. Toxic effects
a. Liver damage – especially in pregnant women
b. Renal damage – may worsen existing disease
c. Demeclocycline may cause nephrogenic diabetes insipidus (and so is used to treat the Syndrome of inappropriate Anti-diuretic Hormone (SIADH)).
d. Pigmentation of the teeth may occur in small children if tetracyclines are given to them or to their mothers during pregnancy.
e. Outdated tetracycline can cause a form of Fanconi’s syndrome.
7. Interactions – when given with dairy foods, antacids, iron compounds, sulcrafate or bismuth compounds, the metal will chelate and decrease the absorption of the antibiotic.
8. Contraindications – administration to children under 8 years old and pregnant or nursing women
CHLORAMPHENICOL
1. Effective against a wide range of bacteria; mostly bacteriostatic; may be bactericidal against Hemophilus, Neisseria and Pneumococcus
2. Given orally and parenterally
3. Due to the risk of aplastic anemia, chloramphenicol is reserved for cases where the infection is resistant to other less toxic antibiotics.
4. The “gray baby” syndrome is seen in neonates, mostly premature, who receive chloramphenicol. It is often fatal.
5. Interactions
a. Chloramphenicol increases half-lives of dicumarol, phenytoin, chlorpropamide and tolbutamide.
b. Its half-life is decreased by rifampin or phenobarbital.
MACROLIDES
1. Examples are erythromycin, azithromycin and clarithromycin.
2. Usually bacteriostatic and effective against Gram-positive organisms, Chlamydia, Mycoplasma and Legionella; azithromycin and clarithromycin also effective against Hemophilus and Mycobacterium-avium-intracellulare.
3. Given orally in capsules or with enteric coating as gastric acid breaks the drug down; also given parenterally (intramuscular injection is painful). Give on an empty stomach.
4. Uses
a. for treatment of infections by the above organisms
b. for treatment of pertussis and prophylaxis of contacts
c. used for prophylaxis in penicillin-sensitive patients, particularly in pregnant women
5. Side effects
a. Gastro Intestinal Tract (GIT) effects can affect compliance – abdominal pain, nausea and vomiting
b. hypersensitivity
c. Cholestatic hepatitis – which is reversible after stopping the drug
6. Interactions – erythromycin increases effects of carbamazepine, steroids, cyclosporine, digoxin, theophylline, valproic acid, warfarin and more – via cytochrome P450
CLINDAMYCIN
1. Bacteriostatic against Gram-positive bacteria, anaerobes, Toxoplasma and Pneumocystis carinii
2. Given orally, topically and parenterally
3. Uses
a. for the treatment of infections caused by the above bacteria
b. for the oral and topical treatment of acne
c. for the oral and topical treatment of bacterial vaginosis
4. Side effects
a. Major cause of pseudomembranous colitis
b. Also see skin rash and when given intravenously, thrombophlebitismay occur
VANCOMYCIN
1. Effective against Staph., Strep., Enterococcus, Corynebacterium and Clostridium
2. Given intravenously; orally for the treatment of pseudomembranous colitis
3. Uses
a. Treatment of pseudomembranous colitis
b. Treatment of infections caused by Methicillin-Resistant Staphylococcus aureus (MRSA)
c. Treatment of infections by above bacteria when other antibiotics fail
4. Side effects - hypersensitivity
5. Toxic effects
a. Ototoxicity – may be reversible
a. “Red man” syndrome – flushing, tachycardia and hypotension – occurs with too rapid intravenous infusion.
b. May be kidney damage if given with nephrotoxic drugs or to patient with renal disorder
BACITRACIN
1. Topical use only due to severe nephrotoxicity if given parenterally
2. Effective against Gram-positive aerobes
3. Uses – eyes, skin
POLYMYXIN B
1. Topical use only due to severe nephrotoxicity if given parenterally
2. Effective against Gram-negative bacteria, especially Pseudomonas
3. Uses – ears, eyes and skin
DRUGS FOR THE TREATMENT OF DISEASES CAUSED BY MYCOBACTERIUM
DRUGS FOR THE TREATMENT OF TUBERCULOSIS
Background
1. First line drugs are isoniazid, rifampin, ethambutol, streptomycin and pyrazinamide – they are the most efficient, have acceptable side effects and will treat most cases of tuberculosis in most people. Treatment is with 2 or 3 agents because use of one agent encourages resistance. There is minimal cross-resistance between the various agents.
2. Second line drugs are used in resistant cases or in patients with AIDS and include ofloxacin, ciprofloxacin, ethionamide, aminosalicylic acid, cycloserine, amikacin, kanamycin and capreomycin. They are only available for parenteral use. Due to ototoxicity and nephrotoxicity, these agents are only used if the first line drugs are not effective. Only one should be given with a first line agent, but not with streptomycin.
3. Different regimens are recommended. The basic regimen is isoniazid with rifampin and pyrazinamide for 2 months and then rifampin and isoniazid for another 4 months. Another possibility is isoniazid and rifampin for 9 months. The Centers for Disease Control (CDC) recommend four drugs together – isoniazid, rifampin, pyrazinamide and ethambutol or streptomycin.
4. The CDC regimen is recommended for those exposed to resistant strains and those with tuberculosis in sites other than the lungs or extensive disease in the lungs.
5. AIDS patients should receive at least the four-drug regimen, and in some cases a fifth or sixth drug may need to be added. Prophylactic treatment with isoniazid (ethambutol and pyrazinamide if exposed to resistant strains) is recommended to AIDS patients with positive Purified Protein Derivative (PPD) tests, anergy or at risk for tuberculosis.
6. In other patients, prophylaxis is recommended for those exposed totuberculosis, those with positive PPD but no clinical disease, those with history of active tuberculosis in the past who did not receive adequate treatment, and patients with anergy who come from a high-risk population. The recommended drug is isoniazid. Pregnant women and patients with active hepatic disease should receive prophylaxis at a later date.
7. The regimen of isoniazid, rifampin and ethambutol is considered to be safe for pregnant women.
Isoniazid
1. Drug of choice in tuberculosis
2. Mechanism of action is unknown.
3. Good oral and parenteral absorption; inactivation is via acetylation. Different populations have different proportions of “rapid” and “slow”acetylators, which influence how quickly the drug is inactivated.
4. Uses
a. Treatment of tuberculosis; usually two or three agents together
b. Alone for prophylaxis of tuberculosis
5. Side effects
a. Side effects include rash, fever, jaundice, hypersensitivity, arthritis,vasculitis, anemia, thrombocytopenia, eosinophilia andagranulocytosis.
b. Neurological side effects include peripheral neuritis, increased risk of convulsions in epileptics, euphoria, memory loss, psychosis, muscle twitches, dizziness, ataxia, paresthesias, stupor and encephalopathy.
c. To minimize neurological side effects, especially in patients with nutritional deficiencies (malnutrition, pregnancy, diabetes, chronic renal failure, elderly), pyridoxine (vitamin B6) is given together with the isoniazid.
d. Hepatotoxicity, which may be fatal, is not uncommon and the risk increases with increasing age. Need to watch very carefully for signs of hepatitis, besides jaundice that is a common side effect.
6. Toxic effects – coma, seizures, metabolic acidosis, hyperglycemia
7. Interactions – isoniazid increases concentrations of phenytoin, especially in slow acetylators. Adjustments as necessary should be made to the dose of phenytoin without changing the dose of isoniazid.
8. Contraindication – relative – hepatic disease
Rifampin
1. Effective against Gram-positive bacteria such as S. aureus, Hemophilus influenzae and Neisseria meningitidis and Gram-negative bacteria such as E. coli, Proteus, Klebsiella and Pseudomonas, as well as Mycobacterium, especially M. tuberculosis, M. kansasii and M. fortuitum
2. Acts by inhibiting RNA polymerase
3. Uses
a. in treatment of tuberculosis, together with isoniazid and others
b. for prophylaxis in people exposed to meningococcemia or H. influenzae type B meningitis
c. in cases of endocarditis or osteomyelitis resistant to other antibiotics
d. in leprosy
4. Given orally
5. Side effects
a. Colors body secretions orange
b. Rash, fever, nausea and vomiting, jaundice
c. Increased side effects are seen if rifampin is given infrequently or in high daily doses – a flu-like syndrome results that may develop into interstitial nephritis, acute tubular necrosis, hemolytic anemia and shock
d. Rifampin induces hepatic microsomal enzymes and so decreases the half-lives of many, many drugs. The most important of these aredigitoxin, quinidine, propanolol, oral anticoagulants, theophylline, barbiturates, oral contraceptives, halothane, methadone and sulfonylureas.
6. Toxic effects - Hepatotoxicity, especially in children, alcoholics, the elderly and patients with liver disease
7. Interactions
a. Is synergistic in vitro with streptomycin and isoniazid
b. Aminosalicylic acid may delay absorption of rifampin – best to give them 8-12 hours apart
8. Contraindications – best not to use in pregnancy or in patients with liver disease
Ethambutol
1. Mechanism of action is not known.
2. Oral absorption is good.
3. Uses – in treatment of tuberculosis together with other drugs
4. Side effects are minimal – blurry vision, rash, fever, headache,pruritus, arthralgia, dizziness, confusion, nausea and vomiting,hyperuricemia
5. Toxic effects - optic neuritis and red-green color blindness that are dose-dependent; should test visual acuity and color blindness before and during treatment with ethambutol
6. Contraindications – children under 5 years old
Streptomycin
1. Aminoglycoside antibiotic
2. Due to resistant bacteria and high toxicity, streptomycin is not often used today.
3. It is used together with two other drugs in disseminated tuberculosis or tuberculitic meningitis.
4. Side effects – rash, fever
5. Toxic effects – damage to cranial nerve VIII and the kidneys
Pyrazinamide
1. good oral absorption
2. uses – together with other drugs for the treatment of tuberculosis
3. side effects – hyperuricemia with clinical gout, arthralgia, nausea and vomiting, loss of appetitie, fever and painful urination
4. Toxic effects - liver disease is common and may be fatal; need to monitor liver function regularly
5. Contraindications – absolute – patient with liver disease
DRUGS FOR THE TREATMENT OF MYCOBACTERIUM AVIUM COMPLEX (MAC)
Background
1. MAC infection is common in AIDS patient where it is a disseminated disease. In patients without AIDS, it is usually restricted to the lungs.
2. Like tuberculosis, the use of one drug increases resistance and so the regiments are 2, 3 or 4 drugs.
3. The basic regimen is ethambutol with either clarithromycin or azithromycin.
4. Prophylaxis with rifabutin for life is recommended for AIDS patients with CD4 count under 100 cells/mm3.
Rifabutin
1. Derivative of rifampin
2. Used especially in AIDS patients
3. Given orally
4. Side effects – rash, nausea and vomiting, neutropenia, orange-colored body fluids
5. Toxic effects – uveitis, arthralgia
6. Like rifampin, induces hepatic microsomal enzymes and decreases concentrations of many drugs
Macrolides
1. Discussed in chapter on antibiotics
2. Examples are clarithromycin and azithromycin.
3. Used in combination with another agent (ethambutol, rifampin, rifabutin, ciprofloxacin, amikacin or clofazimine)
4. Toxic effects – tinnitus, dizziness and transient loss of hearing
Quinolones
1. Discussed in chapter on antibiotics
2. Used in AIDS patients – regimen is ciprofloxacin, clarithromycin, amikacin or rifampin, ethambutol, clofazimine and ciprofloxacin
DRUGS FOR THE TREATMENT OF LEPROSY
Sulfones
1. Most widely used is dapsone; sulfoxone is a derivative of dapsone
2. Dapsone is bacteriostatic for Mycobacterium leprae and is given orally.
3. Side effects – nausea, vomiting, lack of appetite, syndrome similar to infectious mononucleosis with possible mortality
4. Toxic effects – hemolysis, methemoglobinemia
5. A sulfone syndrome – similar to the Jarisch-Herxheimer reaction – may occur, with fever, jaundice, peeling skin, anemia and swollen glands.
Clofazimine
1. Used in MAC, but mainly in leprosy, together with other agents, for dapsone-resistant strains
2. Given orally
3. One side effect seen is red coloring of the skin
For more information on Clinical Research Career Training and Clinical Trials Services please contact Kriger Research Group atinfo@kriger.com or call (866) 757-9791 (USA and Canada) or + 1(416) 630-0038 (Internationally)
Thursday, March 15, 2012


Saturday, November 19, 2011
Amino Acids, Proteins, Enzymes And Why They Are Vital To Health?
Amino acids are organic compounds that combine to form proteins. They are the "building blocks" of the body. Besides building cells and repairing tissue, they form antibodies to combat invading bacteria and viruses; they are part of the enzyme and hormonal system; they build nucleoproteins (RNA & DNA); they carry oxygen throughout the body and participate in muscle activity. When protein is broken down by digestion the result is 22 known amino acids. Eight are essential (cannot be manufactured by the body) and the rest are non essential (can be manufactured by the body with proper nutrition).
Essential amino acids
Tryptophan
Tryptophan is one of the amino acids working as a natural relaxant helping to alleviate insomnia by inducing normal sleep and reducing anxiety and depression. It helps in the treatment of migraine headaches and it helps to reduce cholesterol levels and the risk of artery and heart spasms.
Lysine
Lysine is involved in the adequate absorption of calcium and helps to form collagen (which makes up bone cartilage and connective tissues). It also aids in the production of antibodies, hormones and enzymes. Recent studies have shown that this is one of the amino acids that may be effective against herpes by improving the balance of nutrients that reduce viral growth. A deficiency may result in tiredness, inability to concentrate, irritability, bloodshot eyes, retarded growth, hair loss, anaemia and reproductive problems.
Methionine
Among the amino acids this is the principle supplier of sulphur which prevents disorders of the hair (influences hair follicles and promotes hair growth), skin and nails. It helps lower cholesterol levels and reduces liver fat and protects the kidneys. It’s also a natural chelating agent for heavy metals and it regulates the formation of ammonia and creates ammonia-free urine.
Phenylalaine
Amino acids are important for the nerve system. Phenylalaine is used by the brain to produce Norepinephrine, a chemical that transmits signals between nerve cells and the brain which keeps you awake and alert, reduces hunger pains, functions as an antidepressant and helps to improve memory.
Threonine
Threonine is an important constituent of collagen, elastin, and enamel protein. It helps to prevent fat build-up in the liver and it helps the digestive and intestinal tracts to function more smoothly. It assists metabolism and assimilation.
Valine
This amino acid is said to promote mental vigour, muscle coordination and calm emotions.
Leucine and isoleucine
Amino acids that provide ingredients for the manufacturing of other essential biochemical components in the body, some of which are utilized for the production of energy, stimulants to the upper brain and helping you to be more alert.
Non essential amino acids
Arginine
Studies have shown that this is one of the amino acids which has improved immune responses to bacteria, viruses and tumour cells, promotes wound healing and regeneration of the liver, causes the release of growth hormones and is considered crucial for optimal muscle growth and tissue repair.
Tyrosine
Tyrosine is one of more amoni acids known to transmit nerve impulses to the brain, to help overcome depression, to improve memory, to increase mental alertness and to promote the healthy functioning of the thyroid, adrenal and pituitary glands.
Glycine
Glycine helps to trigger the release of oxygen to the energy requiring cell-making process. It’s also important in the manufacturing of hormones responsible for a strong immune system.
Serine
With other amino acids serine works as A storage source of glucose by the liver and muscles, helps strengthen the immune system by providing antibodies and synthesizes fatty acid sheath around nerve fibres.
Glutamic acid
Considered to be nature's "brain food" for improving mental capacities. It helps to speed the healing of ulcers, gives a "lift" from fatigue, helps to control alcoholism, schizophrenia and the craving for sugar.
Aspartic acid
When ammonia enters the circulatory system it acts as a highly toxic substance which can be harmful to the central nervous system. Aspartic acid aids in the expulsion of harmful ammonia from the body. Recent studies have shown that aspartic acid may increase resistance to fatigue and increase endurance.
Taurine
Helps stabilize the excitability of membranes which is very important in the control of epileptic seizures. Taurine and sulphur are considered to be factors necessary for the control of many biochemical changes that take place in the aging process. Taurine aids in the clearing of free radical wastes.
Cystine
Some amino acids function as antioxidant. Cystine is a powerful aid to the body in protecting against radiation and pollution. It can help to slow down the aging process, to deactivate free radicals and to neutralize toxins. It aids in protein synthesis and presents cellular change. It is necessary for the formation of the skin, which aids in the recovery from burns and surgical operations.
Histidine
Histidine is found abundantly in haemoglobin and has been used in the treatment of rheumatoid arthritis, allergic diseases, ulcers and anaemia. A deficiency can cause poor hearing.
Proline
Proline is extremely important for the proper functioning of joints and tendons and also helps maintain and strengthen heart muscles.
Alanine
Together with other amino acids alanine is an important source of energy for muscle tissue, the brain and central nervous system. It strengthens the immune system by producing antibodies and helps in the metabolism of sugars and organic acids.
The living cell is the site of tremendous biochemical activity called metabolism. This is the process of chemical and physical change which goes on continually in the living organism: build-up of new tissue, replacement of old tissue, conversion of food to energy, disposal of waste materials, reproduction - all the activities that we characterize as "life". An enzyme is a protein that catalyzes, or speeds up, a chemical reaction. Enzymes may speed up reactions by a factor of many thousands. An enzyme, like any catalyst, remains unaltered by the completed reaction and can therefore continue to function. Enzyme activity can be affected by other molecules. (Inhibitors are molecules that decrease or abolish enzyme activity; activators are molecules that increase the activity.) Many drugs are enzyme inhibitors. Aspirin, for example, inhibits an enzyme that produces the inflammation messenger thus suppressing pain and inflammation.
Enzymes are also used in everyday products such as washing detergents, where they speed up chemical reactions involved in cleaning the clothes (for example, breaking down starch stains).
More than 5,000 enzymes are known. To name different enzymes, one typically uses the ending -ase with the name of the chemical being transformed (substrate) (lactase is the enzyme that catalyzes the cleavage of lactose).
All known enzymes are proteins. They are high molecular weight compounds made up principally of chains of amino acids linked together.
Tuesday, June 7, 2011
Terima Kasih kpd semua ( Lecturers for M'sia 2nd Year Students )
Bismillah...salam semua..dan salam imtihan buat mereka yang akan menduduki exam tak lama lg..
Sudah lama ruangan blog ini tidak diedit dan dihiasi dgn coretan drpd penulisnya..haha
Akhirnya, terdetik di hati nak menulis sesuatu dek ketegangan dalam menghabiskan silibus untuk exam pada awal Jun nanti..
Tepat jam 10.10am, ak sampai.di muka pintu dewan kuliah..hehe, maaf terlambat..namun, kelibat Dr Akef masih belum kulihat...menyedari ruangan kuliah khas utk budak2 Malaysia didominasi oleh pihak akhawat, ak melangkah masuk dgn berhati-hati takut tersalah niat..."asyik2 mcm ni je bile combine kls", fikirku sendirian sambil mencari-cari tempat duduk yang kosong dan strategik..hehe..ak kalau bab memilih tempat ni sensitif skit, tak terlalu jauh dan tak terlalu dekat..kalau ak rasa 'confident' sikit sbb dah prepare awal2, ak akan duduk depan..paling depan skali..huhu
Kadar metabolisma badan ak menurun, tp haba yang terhasil masih lg berlegar-legar di sekeliling tubuhku..siapa suruh ak datang lambat, dah tahu rumah tu jauh dan memakan masa, sampai terkejar-kejar ak ketika nak melintas jalan..agak2 lah 'timing' tu..haha...
Selepas beberapa minit ak melabuhkan punggungku di atas kerusi kayu yang panjang itu, berbaris-baris budak2 ikhwah muncul drpd muka pintu..ak tanpa segan silu membuka ruang bagi mereka memenuhi ruang2 kosong yang lain,,,ak masih lg ingat, hanya 5 org ikhwah je yang duduk di barisan hadapan sekali termasuk ak yang menetap di penjuru kanan..hujung sekali..terpinga-pinga ak dibuatnya takut2 tak nampak 'whiteboard' di depan dgn menyeluruh...
10 minit berlalu...mana Prof. ni??..kls dihuni oleh suara2 pelajar yang terdiri drpd pelbagai kadar frekuensi yg berbeza-beza..tp, yg paling membingitkan telinga adalah nada2 drpd 'high frequency'..aarrgh..bisingnya...lantas kusambar buku nota kecil di dalam beg ak dan ak membelek kertas2 sambil mengulangkaji balik tajuk Kidney yg sedia tercatat...
Masa berlalu tanpa kusedari...sehinggalah ku terdengar gemaan suara Dr. Akef di luar dewan/kls...Alhamdulillah sampai jgk, ak dah tak tahan dah dgn suasana ini...silap haribulan, boleh jadi tension tak tentu pasal..haha
Sudah lama ruangan blog ini tidak diedit dan dihiasi dgn coretan drpd penulisnya..haha
Akhirnya, terdetik di hati nak menulis sesuatu dek ketegangan dalam menghabiskan silibus untuk exam pada awal Jun nanti..
...................................................................................................................
Hari ini, ak ada kelas Icterus jam 10am..tiba2, terasa malas pulak sbb dah lama x pergi kelas sbb 'exam leave' dah lama dinikmati..apa2 pun, ini adalah 'last class'..nak tak nak, ak gagahkan kaki untuk melangkah menuju ke Physiology department...Tepat jam 10.10am, ak sampai.di muka pintu dewan kuliah..hehe, maaf terlambat..namun, kelibat Dr Akef masih belum kulihat...menyedari ruangan kuliah khas utk budak2 Malaysia didominasi oleh pihak akhawat, ak melangkah masuk dgn berhati-hati takut tersalah niat..."asyik2 mcm ni je bile combine kls", fikirku sendirian sambil mencari-cari tempat duduk yang kosong dan strategik..hehe..ak kalau bab memilih tempat ni sensitif skit, tak terlalu jauh dan tak terlalu dekat..kalau ak rasa 'confident' sikit sbb dah prepare awal2, ak akan duduk depan..paling depan skali..huhu
Kadar metabolisma badan ak menurun, tp haba yang terhasil masih lg berlegar-legar di sekeliling tubuhku..siapa suruh ak datang lambat, dah tahu rumah tu jauh dan memakan masa, sampai terkejar-kejar ak ketika nak melintas jalan..agak2 lah 'timing' tu..haha...
Selepas beberapa minit ak melabuhkan punggungku di atas kerusi kayu yang panjang itu, berbaris-baris budak2 ikhwah muncul drpd muka pintu..ak tanpa segan silu membuka ruang bagi mereka memenuhi ruang2 kosong yang lain,,,ak masih lg ingat, hanya 5 org ikhwah je yang duduk di barisan hadapan sekali termasuk ak yang menetap di penjuru kanan..hujung sekali..terpinga-pinga ak dibuatnya takut2 tak nampak 'whiteboard' di depan dgn menyeluruh...
10 minit berlalu...mana Prof. ni??..kls dihuni oleh suara2 pelajar yang terdiri drpd pelbagai kadar frekuensi yg berbeza-beza..tp, yg paling membingitkan telinga adalah nada2 drpd 'high frequency'..aarrgh..bisingnya...lantas kusambar buku nota kecil di dalam beg ak dan ak membelek kertas2 sambil mengulangkaji balik tajuk Kidney yg sedia tercatat...
Masa berlalu tanpa kusedari...sehinggalah ku terdengar gemaan suara Dr. Akef di luar dewan/kls...Alhamdulillah sampai jgk, ak dah tak tahan dah dgn suasana ini...silap haribulan, boleh jadi tension tak tentu pasal..haha
...................................................................................................................
Usai ak dan rakan2 keluar kls, ak menjenguk jam yg tertera di handphone..aik..pukul DUA!!..jd, 'lecture' tadi lebih kurang 3 jam lebih lah..fuhh, tidak ku sangka diri ini mampu stay 'alert' lebih drpd sejam, Alhamdulillah...sebelum ini, kls 2 jam pun dah terumbang ambing ak punya tumpuan..inikan pula 3 jam....namun, ak ingin sekali mengucapkan jutaan terima kasih kpd Dr Akef walaupun beliau tidak mengajar budak2 ikhwah tahun ini kerana beliau banyak memberiku inspirasi dan semangat untuk menceburi bidang perubatan pada tahun lepas dan tahun ini juga..(mungkin sbb ni kot ak dapat tahan kls berjam-jam..haha)...last sekali, terima kasih kepada semua Prof2 dan Dr2 yang sudi mencurahkan ilmu dan tenaga kpd kami semua...hanya Allah Swt yang mengetahui betapa kami semua menghargai pemberian anda selama ini......................................................................................................................
'Point' utamaku dalam post ini adalah hanya sekadar untuk mengingati jasa2 para 'Lecturer' yang sudi membanting tenaga tulang empat kerat untuk memahamkan pelajar2 medic Gen 09 tentang ilmu perubatan sehari demi sehari sehinggalah kini..InsyaAllah, me and my very valuable friends will do our very best for the final 2nd year exam 2011..sekian, tk..wasalam~
Wednesday, May 18, 2011
9 Surprising Facts About Your Stomach
When it comes to the tummy, experts say myths abound. How much do you really know about your stomach?
Reviewed by Brunilda Nazario, MD
From those burning, churning feelings that erupt whenever we eat our favorite foods, to the bloating that keeps us from zipping up our jeans, to the gas that can make us the most unpopular person in the elevator, our stomach can be the cause of some major inconveniences, if not some outright health concerns.
Still, experts say most folks know painfully little about how their stomach and their digestive tract operates -- one reason that solving tummy troubles can seem much harder than it has to be.
"There are some very popular misconceptions concerning stomach health, most of which can really lead people astray on how to effectively deal with certain problems," says Mark Moyad, MD, director of preventive and alternative medicine at the University of Michigan Medical Center in Ann Arbor.
Gastroenterologist David Greenwald, MD, agrees. "Sometimes what seems like a complex, difficult or even frightening problem really is a simple one, with a simple solution, if you can separate the myths from the facts," says Greenwald, an associate professor at the Albert Einstein College of Medicine and Montefiore Medical Center in New York City.
To help set the record straight, Greenwald, Moyad, and NYU director of pediatric gastroenterology Joseph Levy, MD, helped WebMD prepare the following gut-busting challenge. Try to separate the myths from the facts to see how much you really know about how to keep your tummy healthy and happy.
1. Myth or Fact: Digestion takes place primarily in the stomach.
Answer: Myth. The major part of the digestive process takes place in the small intestine. The stomach takes in the food, then churns it and breaks it into tiny particles called "chyme." The chyme are then released in small batches into the small intestine, where most digestion occurs, he says.
Contrary to popular belief, Levy says, foods do not digest in the order they are eaten. "Everything lands in the stomach where it's all churned together, and when it's ready it's released into the small intestines together," he says.
2. Myth or Fact: If you cut down on your food intake, you'll eventually shrink your stomach so you won't be as hungry.
Answer: Myth. Once you are an adult, your stomach pretty much remains the same size -- unless you have surgery to intentionally make it smaller. Eating less won't shrink your stomach, says Moyad, but it can help to reset your "appetite thermostat" so you won't feel as hungry, and it may be easier to stick with your eating plan.
3. Myth or Fact: Thin people have naturally smaller stomachs than people who are heavy.
Answer: Myth. While it may seem hard to believe, the size of the stomach does not correlate with weight or weight control. People who are naturally thin can have the same size or even larger stomachs than people who battle their weight throughout a lifetime. "Weight has nothing to do with the size of the stomach. In fact, even people who have had stomach-reducing surgeries, making their tummy no larger than a walnut, can override the small size and still gain weight," says Levy.
4. Myth or Fact: Exercises like sit-ups or abdominal crunches can reduce the size of your stomach.
Answer: Myth. "No exercise can change the size of an organ, but it can help burn the layers of fat that can accumulate on the outside of your body. Plus it can help tighten the muscles in the abdomen, the area of the body lying just south of the diaphragm, that houses the stomach and many other internal organs," says Moyad.
Interestingly, the part of your "belly fat" that can do you the most harm may actually be the fat you don't see. It resides in the "omentum," a kind of internal sheet that lies over and around your internal organs.
"People who are very overweight often have a lot of fat between their organs internally. In fact, in some instances, the liver can become so packed with fat you can develop a form of hepatitis, and in extreme cases, it can stop functioning altogether," says Levy. The good news: A healthy eating plan can not only help you shed the weight you can see, but also the internal fat layers you don't see.
5. Myth or Fact: Foods that contain insoluble fiber (which does not dissolve in water) cause less gas and bloating than foods with soluble fiber (which does dissolve in water).
Answer: Fact. According to Moyad, most folks are astounded to discover that what they perceived as a "gentler" form of fiber -- the soluble kind found in foods like oat bran, beans, peas, and citrus fruits -- can actually cause more gas and bloating than insoluble fiber, found in foods like whole-wheat bread, wheat cereals, cabbage, beets, and carrots. "It is true," says Moyad. "And the reason is that gas and bloating result from intestinal flora that is needed to digest soluble fiber." Since insoluble fiber is not digested at all -- it goes right through you -- there is no interaction with intestinal flora; consequently, no gas is formed.
One caveat to keep in mind: While insoluble fiber won't give you gas, it can increase the frequency and size of bowel movements.
6. Myth or Fact: One way to reduce acid reflux is to lose as little as 2 to 3 pounds.
Answer: Fact. "The less acid that flows back up into your esophagus, the fewer problems you will have clearing it. And believe it or not, losing just 2 pounds of weight from the abdominal area can make a difference -- and pregnancy is about the best example of this," says Moyad. As the baby grows and pushes against the internal organs, heartburn increases; but once the baby is born and the pressure is relieved, the heartburn is, too. "In much the same way, losing even a little bit of belly fat can provide similar relief.
The really good news: Moyad says most people lose weight in the belly area first, so you should see some positive results on your heartburn within a few weeks after starting a weight loss plan.
7. Myth or Fact: Eating before bed can make you gain weight faster than if you eat the same foods during the day.
Answer: Myth. Most experts agree that we gain weight when we take in more calories than we burn up. And while it seems logical that foods we eat during an active day will burn more quickly and more efficiently than foods we eat right before going to sleep, Moyad says weight gain is not based on a 24-hour clock. "It's the total amount you take in over a period of time compared to how much you burn that determines if you will gain weight," says Moyad.
Recent animal studies suggest that avoiding after-dinner snacks may help prevent weight gain. Eating at night may disrupt the body's circadian clock and alter hormones that control appetite and ultimately result in weight gain.
That said, Levy reminds us that when we are fatigued or stressed, eating right before bedtime can make digestion more difficult and may cause more gas, bloating, and heartburn. "There is a 'brain' in the gut that helps to make sure that food is moved through the digestive system at the right pace, in the right amount," says Levy. When we are fatigued -- like most of us are at the end of a busy day -- that 'gut brain' is fatigued as well. So, says Levy, there is a decrease in the number of contractions that move food through the system.
8. Myth or Fact: A 200-calorie snack of peanut butter and crackers is more likely to control your appetite than just eating 200 calories' worth of crackers.
Answer: Fact. The reason: "Fats digest much slower than carbohydrates, and they remain in the stomach longer, which means we naturally feel full longer after eating a snack that contains at least some fat," says Levy.
Additionally, Moyad points out that simple carbohydrates (like crackers, bread, or cookies) elicit a quick rise in blood sugar and insulin levels, which subsequently drop just as quickly, causing dramatic shifts in both mood and appetite. "In short, you find yourself edgy and hungry," says Moyad.
9. Myth or Fact: Beans cause everyone to make excess gas, and there's nothing you can do about it.
Answer: Myth ... sort of! Beans are high in a kind of sugar that requires a certain enzyme to properly digest. "Some people have more if it, some people less. And the less you have, the more gas that will be produced during digestion of beans," says Greenwald. What can help: Studies show that over-the-counter products that add moreof the enzyme needed to break down the sugar in beans as well as other traditionally gassy vegetables can help if taken before you eat. After the fact, you can reduce the gas that forms by taking a product containing simethicone, which, says Greenwald, is a true bubble buster, releasing the surface tension on gas bubbles that form as a result of eating foods that are hard to digest.
Sunday, May 15, 2011
15 Immune Boosting Foods..
1. Elderberry
 An old folk remedy, extract from these dark berries appears to block flu viruses in test tube studies. And a few small studies done in people show it may help you recover more quickly from flu. But scientists caution that further study is needed. The fruit itself is rich in antioxidants and may also have the ability to fight inflammation.
2. Button Mushrooms
Don't dismiss the lowly mushroom as nutrient poor: It has the mineral selenium and antioxidants. Low levels of selenium have been linked to increased risk of developing more severe flu. And the B vitamins riboflavin and niacin, found in these mushrooms, play a role in a healthy immune system. Animal studies have also shown mushrooms to have antiviral, antibacterial, and anti-tumor effects.
3. Acai Berry
 Hawked as a "super food" along with produce like blueberries, the little acai berry's dark color signals that it is high in antioxidants called anthocyanins. While the acai is not scientifically linked to specific disease- or illness-fighting ability, antioxidants may help your body fight aging and disease. Acai berries can be found most often in juice or smoothie form, or dried and mixed with granola.
4. Oysters
 Aphrodisiac? Immune boosters? Maybe both, thanks to the mineral zinc that's found in oysters. Low zinc levels have been associated with male infertility. And zinc appears to have some antiviral effect, although researchers can't explain why. However, they do know it is important to several immune system tasks including healing wounds.
5. Watermelon
Hydrating and refreshing, ripe watermelon also has plenty of a powerful antioxidant, glutathione. Known to help strengthen the immune system so it can fight infection, glutathione is found in the red pulpy flesh near the rind.

6. Cabbage
This is another source of immune-strengthening glutathione. And cabbage is easy and inexpensive to find during the winter months when it's in season. Try adding cabbages of any variety (white, red, Chinese) to soups and stews to sneak in extra antioxidants and boost your meal's nutritional value.

7. Almonds
A handful of almonds may shore up your immune system from the effects of stress. A recommended 1/4 cup serving carries nearly 50% of the daily recommended amount of vitamin E, which helps boost the immune system. And they have riboflavin and niacin, B vitamins that may help you bounce back from the effects of stress.


8. Grapefruit
Grapefruits have a good amount of vitamin C. But science has yet to prove that you can easily get enough vitamin C through foods alone, without supplementation, to help treat cold and flu. However, grapefruit is packed with flavonoids -- natural chemical compounds that have been found to increase immune system activation. Dislike grapefruits? Try oranges or tangerines.
9. Wheat Germ
Wheat germ is the part of a wheat seed that feeds a baby wheat plant, so it is full of nutrients. It has zinc, antioxidants, and B vitamins among other vital vitamins and minerals. Wheat germ also offers a good mix of fiber, protein, and some good fat. Substitute wheat germ for part of the regular flour called for in baked goods and other recipes.
10. Low-Fat Yogurt
A daily cup may reduce your chances of getting a cold. Look for labels listing "live and active cultures." Some researchers believe they may stimulate your immune system to fight disease. Also look for vitamin D. Recent studies have found a link between low vitamin D levels and an increased risk of cold and flu.
11. Garlic
Garlic offers several antioxidants that battle immune system invaders. Among garlic's targets are H. pylori, the bacteria associated with some ulcers and stomach cancer. Cooking tip: Peel, chop and let sit 15 to 20 minutes before cooking to activate immune-boosting enzymes.
12. Spinach
Known as a "super food," spinach is nutrient-rich. It has folate, which helps your body produce new cells and repair DNA. And it boasts fiber, antioxidants, such as vitamin C, and more. Eat spinach raw or lightly cooked to get the most benefit.
 13. Tea
Green or black? Both are loaded with disease-fighting polyphenols and flavonoids. These antioxidants seek out cell-damaging free radicals and destroy them. Caffeinated and decaf work equally well.

14. Sweet Potato
Like carrots, sweet potatoes have the antioxidant beta-carotene, which mops up damaging free radicals. Sweet potatoes also boast vitamin A, which is linked to slowing the aging process and may reduce the risk of some cancers.

15. Broccoli
Easy to find at the grocery store and incorporate into meals, broccoli is an immune-boosting basic. One study reported a chemical in broccoli helped stimulate the immune systems of mice. Plus, it's full of nutrients that protect your body from damage. It has vitamins A, vitamin C, and glutathione. Add some low-fat cheese to round out a side dish with immune-enhancing B vitamins and vitamin D.
Saturday, May 14, 2011
Understanding Thyroid Symptoms and Solutions
(A)When Your Thyroid Goes Awry
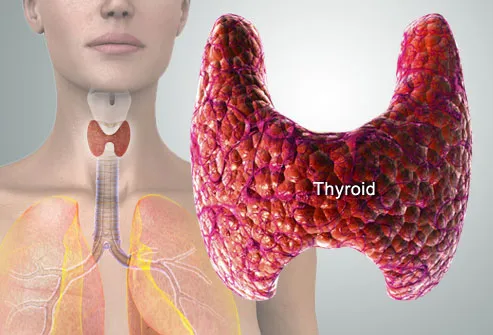 Does fatigue drag you down day after day? Do you have brain fog, weight gain, chills, or hair loss? Or is the opposite true for you: Are you often revved up, sweaty, or anxious? Your thyroid gland could be to blame. This great regulator of body and mind sometimes goes haywire, particularly in women. Getting the right treatment is critical to feel your best and avoid serious health problems.
(B)What Is the Thyroid Gland?
The thyroid is a butterfly-shaped gland in the front of the neck. It produces hormones that control the speed of your metabolism -- the system that helps the body use energy. Thyroid disorders can slow down or rev up your metabolism by disrupting the production of thyroid hormones. When hormone levels become too low or too high, you may experience a wide range of symptoms.
(C)Symptoms
1. Symptom: Weight Gain or Loss
An unexplained change in weight is one of the most common signs of a thyroid disorder. Weight gain may signal low levels of thyroid hormones, a condition called hypothyroidism. In contrast, if the thyroid produces more hormones than the body needs, you may lose weight unexpectedly. This is known as hyperthyroidism. Hypothyroidism is far more common.
2. Symptom: Swelling in the Neck
A swelling or enlargement in the neck is a visible clue that something may be wrong with the thyroid. A goiter may occur with either hypothyroidism or hyperthyroidism. Sometimes swelling in the neck can result from thyroid cancer or nodules, lumps that grow inside the thyroid. It can also be due to a cause unrelated to the thyroid.
3. Symptom: Changes in Heart Rate
Thyroid hormones affect nearly every organ in the body and can influence how quickly the heart beats. People with hypothyroidism may notice their heart rate is slower than usual. Hyperthyroidism may cause the heart to speed up. It can also trigger increased blood pressure and the sensation of a pounding heart, known as heart palpitations.
4. Symptom: Changes in Energy or Mood
Thyroid disorders can have a noticeable impact on your energy level and mood. Hypothyroidism tends to make people feel tired, sluggish, and depressed. Hyperthyroidism can cause anxiety, problems sleeping, restlessness, and irritability.
5. Symptom: Hair Loss
Hair loss is another sign that your thyroid hormones may be out of balance. Both hypothyroidism and hyperthyroidism can cause hair to fall out. In most cases, the hair will grow back once the thyroid disorder is treated.
6. Symptom: Feeling Too Cold or Hot
Thyroid disorders can disrupt the ability to regulate body temperature. People with hypothyroidism may feel cold more often than usual. Hyperthyroidism tends to have the opposite effect, causing excessive sweating and an aversion to heat.
Other Symptoms of Hypothyroidism
Hypothyroidism can cause many other symptoms, including:
- -Dry skin and brittle nails
- -Numbness or tingling in the hands
- -Constipation
- -Heavy menstrual periods
Other Symptoms of Hyperthyroidism
Hyperthyroidism can also cause additional symptoms, such as:
- Muscle weakness or trembling hands
- Vision problems
- Diarrhea
- Irregular menstrual periods
(D)Thyroid Disorder or Menopause?
Because thyroid disorders can cause changes in your menstrual cycle and mood, the symptoms are sometimes mistaken for menopause. If a thyroid problem is suspected, a simple blood test can determine whether the true culprit is menopause or a thyroid disorder – or a combination of the two.
(E)Test & Diagnose
Who Should Be Tested?
Everyone should be screened for thyroid dysfunction every five years, beginning at age 35, according to the American Thyroid Association. People with symptoms or risk factors may need tests more often. Hypothyroidism more frequently affects women over age 60. Hyperthyroidism is also more common in women and in people over 60. A family history raises your risk of either disorder.
Thyroid Neck Check
A careful look in the mirror may help you spot an enlarged thyroid that needs a doctor's attention. Tip your head back, take a drink of water, and as you swallow, examine your neck below the Adam's apple and above the collarbone. Look for bulges or protrusions, then repeat the process a few times. See a doctor promptly if you see a bulge or lump.
Diagnosing Thyroid Disorders
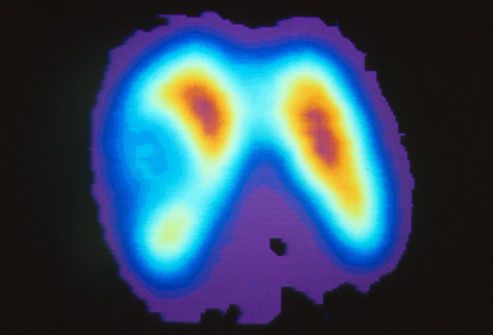
If your doctor suspects a thyroid disorder, a blood test can help provide an answer. This test measures the level of thyroid stimulating hormone (TSH), a kind of master hormone that regulates the work of the thyroid gland. If TSH is high, it typically means that your thyroid function is too low (hypothyroid). If TSH is low, then it generally means the thyroid is overactive (hyperthyroid.) Your doctor may also check levels of other thyroid hormones in your blood. In some cases, imaging studies are used and biopsies are taken to evaluate a thyroid abnormality.
(F)Hypothyroidism
Hashimoto's Disease
The most common cause of hypothyroidism is Hashimoto's disease. This is an autoimmune disorder in which the body attacks the thyroid gland. The result is damage to the thyroid, preventing it from producing enough hormones. Hashimoto's disease tends to run in families.
Other Causes of Hypothyroidism
In some cases, hypothyroidism results from a problem with the pituitary gland, which is at the base of the brain. This gland produces thyroid-stimulating hormone (TSH), which tells the thyroid to do its job. If your pituitary gland does not produce enough TSH, your levels of thyroid hormones will fall. Other causes of hypothyroidism include temporary inflammation of the thyroid or medications that affect thyroid function.
(G)Hyperthyroidism
Graves' Disease
The most common cause of hyperthyroidism is Graves' disease. This is an autoimmune disorder that attacks the thyroid gland and triggers the release of high levels of thyroid hormones. One of the hallmarks of Graves' disease is a visible and uncomfortable swelling behind the eyes.
Other Causes of Hyperthyroidism
Hyperthyroidism can also result from thyroid nodules. These are lumps that develop inside the thyroid and sometimes begin producing thyroid hormones. Large lumps may create a noticeable goiter. Smaller lumps can be detected with ultrasound.
(H)Thyroid Disorder Complications
When left untreated, hypothyroidism can raise your cholesterol levels and make you more likely to have a stroke or heart attack. In severe cases, very low levels of thyroid hormones can trigger a loss of consciousness and life-threatening drop in body temperature. Untreated hyperthyroidism can cause serious heart problems and brittle bones.
(I)Treatment
Treating Hypothyroidism
 If you are diagnosed with hypothyroidism, your doctor will most likely prescribe thyroid hormones in the form of a pill. This usually leads to noticeable improvements within a couple of weeks. Long-term treatment can result in more energy, lower cholesterol levels, and gradual weight loss. Most people with hypothyroidism will need to take thyroid hormones for the rest of their lives.
Treating Hyperthyroidism
The most common treatment for hyperthyroidism is antithyroid medication, which aims to lower the amount of hormones produced by the thyroid. The condition may eventually go away, but many people need to remain on medication for the long term. Other drugs may be given to reduce symptoms such as rapid pulse and tremors. Another option is radioactive iodine, which destroys the thyroid gland over the course of 6 to 18 weeks. Once the gland is destroyed, or removed by surgery, most patients must begin taking thyroid hormones in pill form.
Surgery for Thyroid Disorders
Removing the thyroid gland can cure hyperthyroidism, but the procedure is only recommended if antithyroid drugs don't work, or if there is a large goiter. Surgery may also be recommended for patients with thyroid nodules. Once the thyroid is removed, most patients require daily supplements of thyroid hormones to avoid developing hypothyroidism.
(J)What About Thyroid Cancer?
Thyroid cancer is uncommon and is among the least deadly. The main symptom is a lump or swelling in the neck, but less than 10 % of thyroid nodules turn out to be cancerous. When thyroid cancer is diagnosed, it is most often treated with surgery followed by radioactive iodine therapy or external radiation therapy.
Subscribe to:
Posts (Atom)